Can Hyperproteinemia Affect the Anion Gap?
What Is an Anion Gap?
The anion gap is a derived value used in laboratory interpretation to help assess acid-base balance and identify certain acid-base disorders. It compares against the main measured electrolytes in blood, especially sodium, chloride, and bicarbonate, to estimate the balance between unmeasured positively and negatively charged particles in the bloodstream.
In simple terms, the anion gap reflects charge balance in a blood sample. A normal value suggests the measured ions are in a typical relationship, while an abnormal result can be a diagnostic clue for conditions such as metabolic acidosis or a protein-related change in serum chemistry. Because the result comes from a formula rather than a direct measurement, understanding the underlying pathophysiology matters.
The anion gap is often used as a screening test during workups of unexplained illness. It does not diagnose a disease by itself, but it helps clinicians think through the cause of an electrolyte imbalance and decide what to test next.
How an Anion Gap Calculator Works
An anion gap calculator uses values from standard blood test results to compute the anion calculation. In most cases, it uses serum sodium, serum bicarbonate, and serum potassium, though potassium is occasionally left out depending on the formula employed by the lab or calculator. The goal is to determine the difference between observed cations and anions.
A typical version of the formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some calculators also incorporate potassium, which slightly changes the result. Whatever the formula, the key anion gap idea is the same: the calculation helps detect shifts in electrolytes that may suggest an underlying problem with acid-base status.
Using an anion gap calculator is helpful because it reduces manual errors and gives a rapid estimate of whether the result is within the expected reference range. Still, the number should always be assessed with the rest of the blood chemistry panel, not alone.
Can Hyperproteinemia Affect the Anion Gap?
Indeed, hyperproteinemia can influence the anion gap, and in many cases it may result in a low anion gap. The effect depends on the nature and quantity of protein present, especially the balance of albumin, paraproteins, and other plasma proteins. This is where the clinical importance becomes important: not all protein elevations affect the anion gap in the same way.
This protein is one of the most important unmeasured anions in blood. When albumin is low, the anion gap may decrease. But hyperproteinemia can also involve excess abnormal proteins, especially paraproteins, which may respond differently from normal albumin. Some of these proteins can carry a positive charge and lower the apparent anion gap by changing the overall charge balance in serum.
This is why a protein-related abnormal result can be a valuable diagnostic clue. In some cases, hyperproteinemia points to a broader systemic disease, and the anion gap calculator becomes one piece of the diagnostic interpretation rather than the final answer.
How Protein Abnormalities May Change Lab Results
Protein abnormalities can affect lab results because proteins help shape the electrolyte environment of blood. Some of these proteins act as cationic proteins, while others are closer to negatively charged proteins. When the level or form of protein varies, the measured electrolyte balance can move even if sodium, chloride, and bicarbonate appear only mildly changed.
In practical terms, this means an increase in abnormal proteins can cause a measurement artifact or a true biochemical shift. A lab artifact does not mean the result is useless; it means the number may not show the full clinical picture without context. That is why laboratory interpretation should always take into account protein concentration, acid-base status, and the patient’s overall condition.
Hyperproteinemia may also affect routine assays in ways that influence how results are reported. While modern laboratory methods are highly reliable, no test is perfect. A pattern that seems inconsistent with the patient’s symptoms may suggest a lab artifact, a protein-related shift, or both. Understanding this helps avoid overcalling acid-base disorders or missing an important underlying diagnosis.
Typical Causes of Hyperproteinemia
Different conditions can cause hyperproteinemia, and the cause often shapes the effect on the anion gap. One of the simplest causes is dehydration, which reduces plasma water and makes proteins appear more concentrated. In that situation, the protein concentration rises relative to the fluid portion of blood, but the clinical effect on the anion gap may be modest unless other abnormalities are present.
More significant causes include multiple myeloma and monoclonal gammopathy, both of which can increase abnormal immunoglobulins in the blood. These paraproteins may alter charge balance and create a low anion gap. This is a classic laboratory interpretation pitfall because the anion gap may be the first clue that leads to further workup.
Chronic inflammation can also increase total protein by increasing certain globulins. In these cases, hyperproteinemia may reflect a chronic systemic disease rather than a primary blood disorder. The pattern of protein changes, along with the rest of the serum chemistry, helps determine whether the finding is benign, transient, or clinically important.
Decreased Anion Gap vs Increased Anion Gap: What to Watch For
A low anion gap is the pattern most often linked to hyperproteinemia, especially when paraproteins are present. Excess proteins can lower the calculated gap by shifting the balance of unmeasured ions. In contrast, high anion gap metabolic acidosis usually points to excess acids in the blood, such as lactate or ketones, and is not typically caused by protein excess alone.
This distinction matters because a high gap and a low gap have different clinical significance. A low gap may suggest protein abnormalities, medication effects, or a lab-related issue, while a high gap more often suggests metabolic acidosis. That said, both can occur in complex illness, so the result should always be viewed alongside symptoms and the rest of the panel.
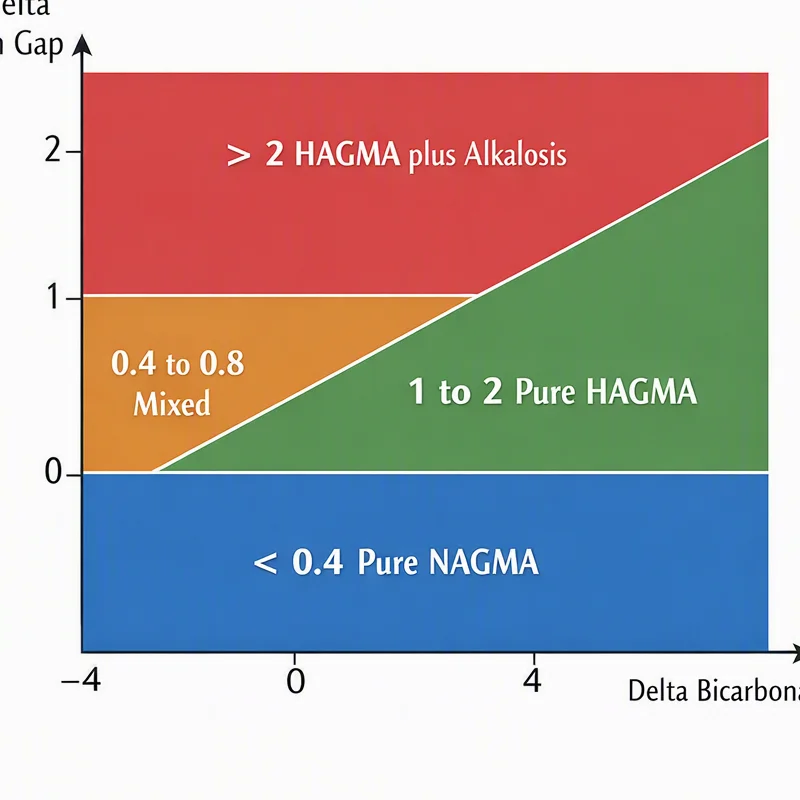
Albumin correction is especially useful when a low albumin level might be hiding the true acid-base status. Since albumin is a major unmeasured anion, low albumin can lower the anion gap and make the value seem less concerning than it really is. Correcting for albumin helps estimate a corrected anion gap and makes the result more accurate for detecting acid-base disorders.
Interpreting Findings Within Clinical Context
Interpreting the anion gap correctly requires reviewing more than one number. The most useful clues often come from serum albumin, total protein, and the full blood chemistry panel. If total protein is high and the anion gap is low, hyperproteinemia becomes more relevant. If albumin is low, the gap should be recalculated before reaching conclusions about acid-base status.
Clinicians also consider the broader acid-base status. For example, a patient with metabolic acidosis and a normal gap may still have a serious illness, while a low anion gap with no symptoms may indicate a protein-related issue or an artifact. The same number can mean something different depending on the rest of the blood test findings.
Here is where anion gap calculator is most useful: it gives a quick starting point for diagnostic interpretation, but the meaning of the result depends on the clinical context. A single number cannot explain the whole story. Symptoms, medications, hydration, kidney function, and protein studies all influence the final interpretation.
When to Recheck or Add More Lab Tests
If the result appears unusual, repeat lab testing is commonly the starting point. Rechecking the sample can help rule out specimen issues, handling problems, or a minor calculation discrepancy. A repeat result also helps determine whether the abnormality is persistent or temporary.
When protein abnormalities are suspected, protein electrophoresis is a standard next test. It can help detect monoclonal proteins and separate causes such as multiple myeloma or monoclonal gammopathy from more general protein elevation. In some cases, a complete complete metabolic panel or other specific blood studies are needed to clarify the clinical picture.
The decision to order more tests should carefully rely on clinical correlation. If the patient feels well and the abnormality is mild, the finding may not require immediate action. If symptoms, kidney issues, anemia, bone pain, or other signs suggest a plasma cell disorder, additional testing becomes anion gap calculation more relevant. The anion gap should guide evaluation, not take its place.
FAQ: Hyperproteinemia and Anion Gap
Can hyperproteinemia lower the anion gap?
Yes, it can. Hyperproteinemia can reduce the anion gap, especially when the elevated proteins are paraproteins or other positively charged proteins. These proteins can alter charge balance and create a low anion gap on laboratory testing.
Does hyperproteinemia cause a high or low anion gap?
It typically causes a reduced anion gap rather than a high one. A high anion gap metabolic acidosis usually points to excess acid buildup, while protein excess is more likely to lower the calculated gap.
Should albumin be corrected when using an anion gap calculator?
Yes, albumin correction is important to do when serum albumin is low. Since albumin strongly affects the anion gap, correcting for it can reveal the corrected anion gap and improve diagnostic interpretation.
What laboratory situations can cause the anion gap appear abnormal?
Several lab factors can influence the result, like testing artifact, alterations in electrolytes, low serum albumin, and abnormal plasma proteins. Checking the full blood chemistry panel helps reveal whether the abnormal result is real or misleading.
When should additional testing be done after an abnormal anion gap result?
Additional testing is warranted when the abnormality is ongoing, unaccounted for, or paired with symptoms or other abnormal blood test results. Protein electrophoresis, repeat lab testing, and a complete metabolic panel are typical follow-up studies when hyperproteinemia or a plasma cell disorder is suspected.

